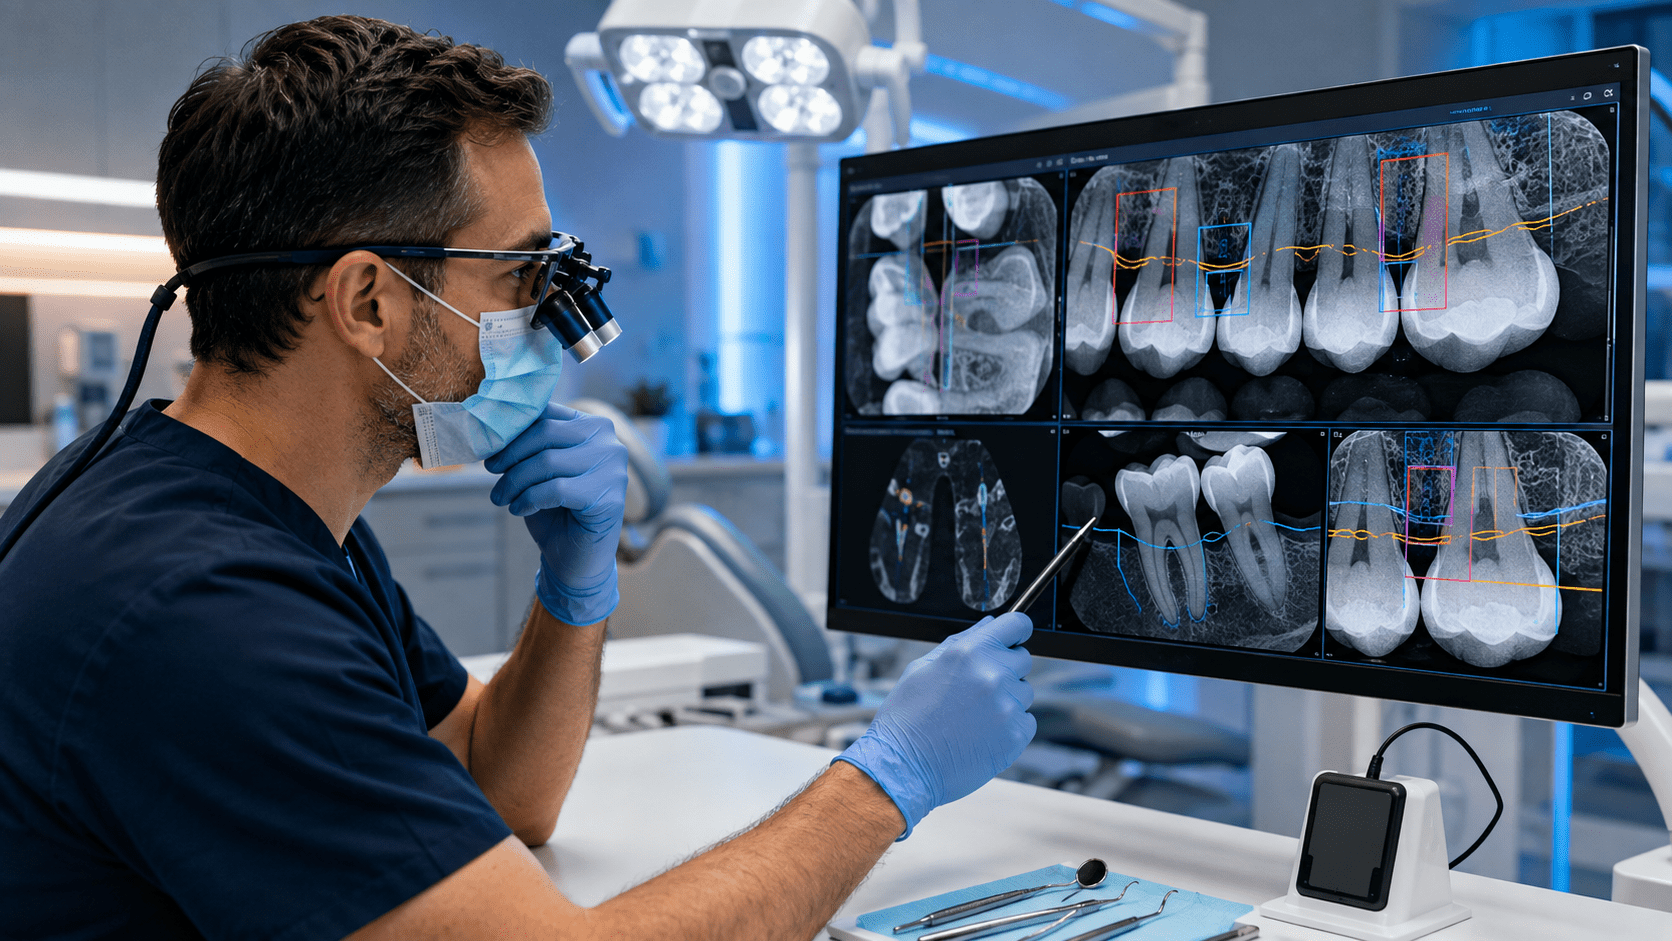
Evaluate these tools on four questions: what regulatory status the product holds and for exactly which task, whether validation exists on images resembling the ones you produce, how many flags you end up adjudicating in a normal day, and how the output fits your workflow and your patient conversations. The diagnosis stays yours no matter what appears on the screen, and that single fact should shape how you weigh every claim a vendor makes.
Treat the output as a prompt to look again, not as an authority.
What does regulatory status actually tell you?
Ask for the specific clearance or authorization the product holds, the exact wording of the indication it covers, and the identifier you can use to look it up yourself. Then look it up yourself, with the regulator, rather than accepting a brochure summary.
Two follow-ups matter. First, what does the software display that falls outside the cleared indication? Second, is the version being sold to you the version that was reviewed? These tools update frequently, and that is a fair thing to ask about in writing.
What validation should you ask to see?
Request the actual published validation rather than the summary slide.
- What images was it built and tested on? Ask whether your own sensor type, image quality, and patient population were represented in the testing.
- What was the reference standard? Ask what the algorithm’s output was compared against, and who decided what counted as correct. That comparison caps the meaning of everything reported downstream.
- Detection rate and false alarm rate, reported separately. A single blended figure hides the tradeoff between them. If only one is offered, ask why.
- Was the validation independent of the vendor?
- Did the tested population resemble the one in your chairs?
Be alert when catch rate is marketed by itself. A tool tuned to miss nothing will flag a great deal.
What does the flag burden look like in daily use?
This is the question that determines whether the software gets used or quietly switched off.
Run a trial on your own images before you buy. Take a set of existing radiographs across a normal mix of your patients, run them through, and count how many flagged findings you disagree with. Multiply that by your daily radiograph volume, and you have a real estimate of the extra work you are signing up for.
Then ask whether thresholds are adjustable, whether you can dismiss a finding, and whether dismissals are recorded. Then ask what your record of dismissals would look like if a case were ever reviewed later, and put that question to your malpractice carrier before you deploy anything.
How should it change the patient conversation?
A colored box on a radiograph is easy for a patient to see and easy for a patient to over-read.
If you show the output to patients, say plainly what it is: a detection aid that you have reviewed and either agree or disagree with. Anything you put on the screen should be something you have independently confirmed and are prepared to explain in your own words.
What about data and privacy?
Ask where images are processed, whether they leave your network, whether the vendor uses your patient images to improve their models, and whether you can decline that. Get the appropriate agreements in place and have someone qualified review them against your own privacy obligations.
Also ask what happens to your access if the vendor is acquired or shuts down. In a young category, that question is neither rude nor hypothetical.
FAQ
Does this software reduce liability or increase it?
Neither on its own, because the diagnosis remains yours. Disagreeing with a flag is ordinary clinical judgment, but how that disagreement is recorded is worth deciding deliberately. Talk to your malpractice carrier about documentation practices before you deploy, rather than after a case is questioned.
Can I use the output to support a claim to a payer?
Ask your payers directly and get the answer in writing, because their positions differ and change. Do not build a case presentation on the assumption that a flag strengthens anything, and do not accept a vendor’s characterization of what payers accept without checking it yourself.
Should a general practice adopt this now or wait?
Decide it on your own radiograph volume and your appetite for reviewing flags. Run a genuine trial on your own images first, set a date to revisit whether anyone is still using it, and be willing to stop if the answer on that date is no.